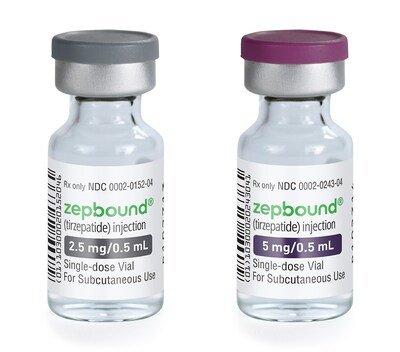
GLP-treatment could start to become highly personalized: As Horn put it to me, somebody with obstructive sleep apnea may still want to take Zepbound because that drug has proven effective for both that condition and weight loss at the same time
Are there any ongoing studies related to semaglutide
Zepbound should be discontinued if pancreatitis is suspected
Tirzepatide may be favored when: Maximum weight loss is the primary goal and cost/insurance isn't a barrier A patient has type 2 diabetes and would benefit from tirzepatide's strong glycemic effects A patient didn't achieve adequate results on semaglutide Semaglutide may be favored when: Cost or insurance coverage strongly favors semaglutide A patient's prescriber has a longer track record of clinical experience with the drug (semaglutide has been used clinically for weight loss for longer) A patient tolerates GLP-1-only therapy well and doesn't need the added GIP effect Neither may be appropriate when: A patient has a personal or family history of medullary thyroid carcinoma or MEN2 syndrome A patient is pregnant, breastfeeding, or planning pregnancy soon A patient has a history of pancreatitis or certain GI conditions, without further evaluation A doctor or obesity-medicine specialist will weigh medical history, current medications, lab work, weight-loss goals, and cost before recommending either drug and will monitor treatment over time, adjusting the plan as needed

They believe theyre seeing the real Amy. They assume the transformation is achievable