fermentum GB102 strain reduced the weight regain when discontinuing dulaglutide drugs, as well as maintaining muscle mass, positioning it as a potential solution to this widespread problem
Furthermore, long-term studies focusing on safety, efficacy, and patient-specific factors will be essential to translate these innovations into viable therapeutic options

During GLP-1associated weight loss, lean-mass changes are typically adaptive and preventable , not degenerative. GLP-1 Body Composition Changes: What Clinical Trials Show About Muscle Loss Clinical trials and body-composition sub-studies of semaglutide and tirzepatide consistently demonstrate: Fat mass accounts for most weight lost during treatment. Lean mass may decrease , particularly without resistance training or adequate protein intake. In many patients, the proportion of lean mass relative to total body weight is preserved or improved , because fat loss exceeds lean loss. Key clinical insight: GLP-1/GIP therapies improve overall body composition by preferentially reducing fat massnot by causing muscle breakdown. Lean mass refers to all the non-fat tissues in the bodyprimarily skeletal muscle , but also organs, bones, connective tissue, and body waterthat support metabolism, movement, and overall physical function
[ 1 ] suggested that, without histologic signs of malignancy, adjuvant treatment should not be performed and only strict radiologic and clinical follow-up is required
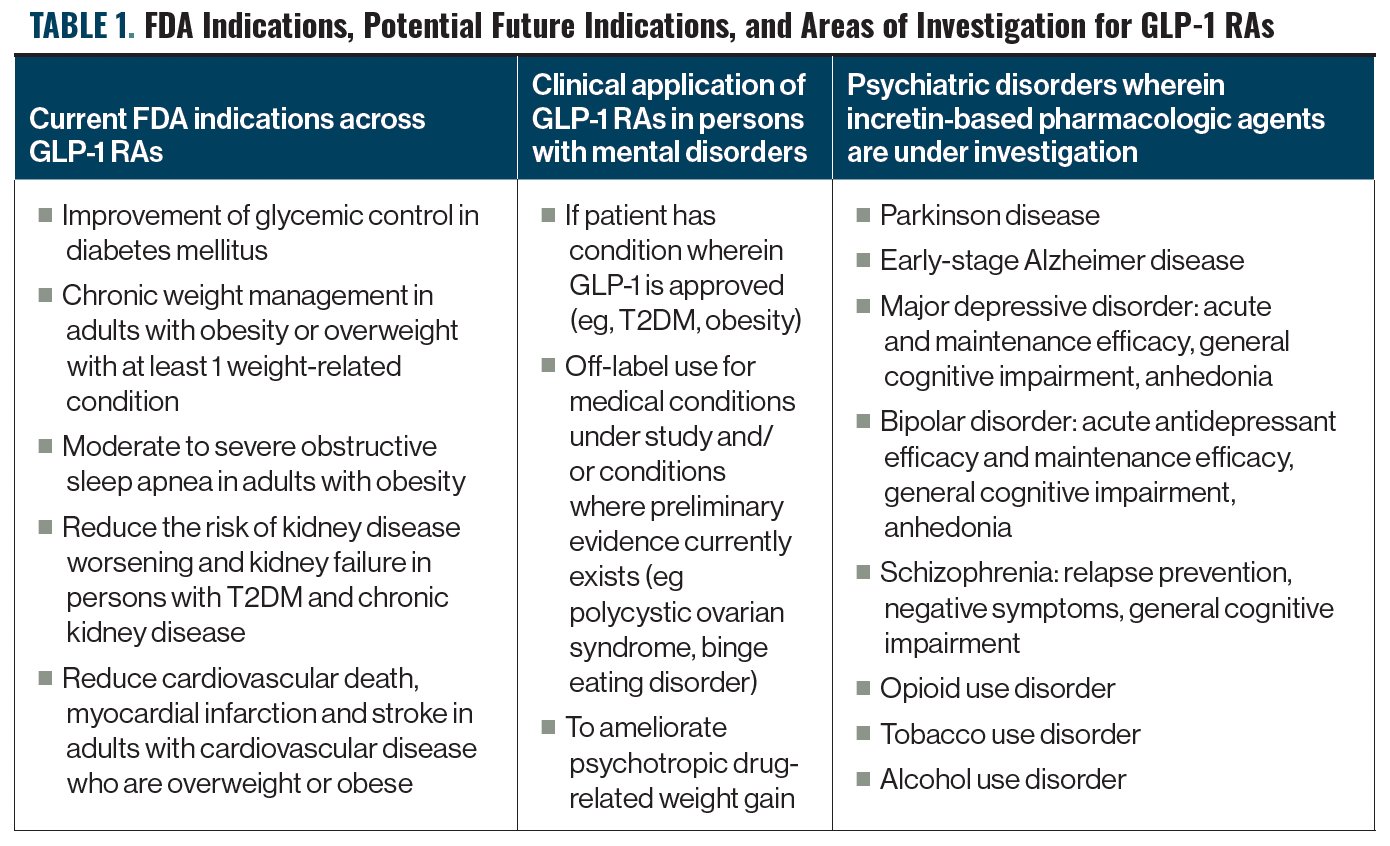
FDA labels approve GLP-1 weight management at BMI 30 alone or BMI 27 with a weight-related condition